Infant feeding practices in Peel
- Exclusive breastfeeding has decreased
- One third of mothers attended a prenatal class in 2024
- Most infants were given a vitamin D supplement
- Most infants started solids within the recommended time frame
- References
- Appendix A: Methods and notes
- Terminology
Peel Public Health works to support parents to achieve their feeding goals while promoting healthy practices. Information and resources are available for families to learn more about feeding their baby. Families can also talk to a public health nurse.
The Peel Infant Feeding Survey was most recently conducted in 2024 and key findings are summarized.
The terms “mother”, “women”, and “breast milk” and “breastfeeding” are used throughout this report to stay consistent with the language used in the survey tools. People with various gender identities can get pregnant and have children and may be included in these data.
Exclusive breastfeeding has decreased
In 2024, mothers exclusively breastfeeding their infants was lower than in 2019 at all measured time points between hospital discharge and 5 months of age. (Refer to terminology for descriptions of these terms)
- Infants exclusively breastfed at hospital discharge decreased from 49% in 2019 to 32% in 2024.
- By 5 months of age, only 10% of infants were exclusively breastfed in 2024 vs. 17% in 2019.
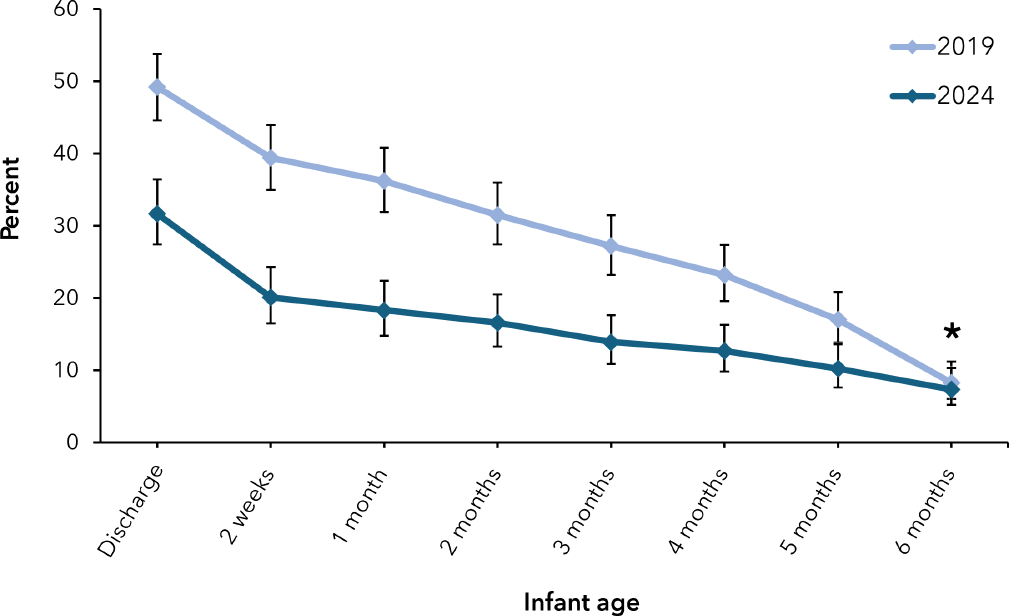
The proportion of Peel mothers exclusively breastfeeding their infants decreased between 2019 and 2024 for all time points from discharge to 5 months after birth.
* Use estimates with caution.
Notes: Vertical bars represent 95% confidence intervals.
Home births are excluded from the first time point, ‘discharge’, but included in all future time points.
Based on multiple survey questions, exclusive breastfeeding at each time point includes those who indicated they had ever breastfed and had not yet introduced any liquids or solids other than breast milk. Infants who were introduced to liquids other than breast milk in hospital were considered not exclusively breastfed from discharge onwards.
Source: Peel Infant Feeding Survey, 2019, 2024, Peel Public Health.
The decline in exclusive breastfeeding was accompanied by other changes
Between 2019 and 2024:
- Infants who were given formula in hospital increased from 43% to 65%.
- Mothers who introduced formula to their infants within 2 weeks of hospital discharge or a home birth increased from 49% to 67%.
- Mothers who had intended to only feed breast milk for the first 4 weeks decreased from 73% to 64%.
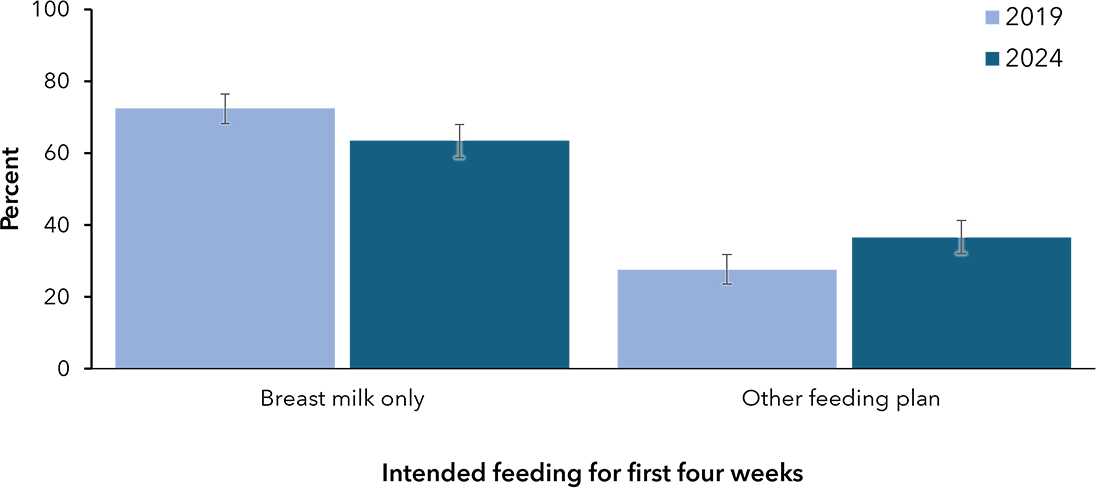
The proportion of Peel mothers who intended to exclusively breastfeed their infant for the first four weeks of life decreased between 2019 and 2024.
Notes: Vertical bars represent 95% confidence intervals.
Other feeding plan combines the following response options: formula only; combination of breast milk and formula; combination of foods; I did not have a feeding plan.
Source: Peel Infant Feeding Survey, 2019, 2024, Peel Public Health.
Mothers felt like they didn’t have enough milk
In 2024, mothers feeling they did not have enough milk was the number one reason for:
- Introducing formula after discharge (55%).
- Introducing liquids other than breast milk in hospital (47%).
- Stopping breastfeeding (68%).
- Experiencing difficulties or concerns with breastfeeding (52%).
Latching was another commonly reported difficulty or concern with breastfeeding
This was also frequently reported as a reason for introducing liquids other than breastmilk in hospital and stopping breastfeeding.
Difficulty accessing breastfeeding services increased
Mothers who reported they were unable to access a breastfeeding service after hospital discharge or a home birth increased from 15% in 2019 to 31% in 2024.
- However, demand was similar as mothers who reported they would have benefited from a breastfeeding service was similar between 2019 (50%) and 2024 (53%).
- Mothers who reported they used a breastfeeding service after discharge or a home birth was also similar between 2019 (47%) and 2024 (47%).

Some breastfeeding practices remained consistent
Mothers who reported receiving support with breastfeeding in hospital was similar between 2019 (86%) and 2024 (85%). Refer to additional graphs.
Mothers who were providing any breast milk at all time points was similar.
- At 2 weeks of age, 96% of mothers were providing any breast milk in 2019 and 97% in 2024.
- At 6 months of age, 70% provided any breast milk in 2024 which was similar to 68% in 2019.
Most mothers who introduced formula within the first 2 weeks still reported providing breast milk for more than half of feedings (2019: 63%; 2024: 63%).
Breastfeeding has health, social and economic benefits
Breastfeeding reduces the incidence and severity of some infections and reduces the risk of infant mortality. Breastfeeding has also been associated with decreased risk of some chronic diseases among mothers (for example, certain types of cancer) and children (for example, asthma) (refer to reference 1-2).
Additionally, as the affordability of infant formula has declined with the monthly average retail price of infant formula in Canada increasing by 62% between 2017 and 2024 (refer to reference 3), breast milk continues to provide optimal nutrition at a lower cost.
Public health plays an important role in increasing the proportion of mothers exclusively breastfeeding
Mothers need support shortly after hospital discharge to address challenges with breastfeeding including not having enough milk and latching concerns.
Additionally, there continues to be a strong need for breastfeeding programs and services after discharge.
One third of mothers attended a prenatal class in 2024
Most prenatal classes had similar content and delivery
- 83% covered the topic of breastfeeding, according to those who attended.
- 65% were delivered online with an instructor, while less were delivered in person or online self-led.
In 2024, 16% of mothers reported receiving no prenatal care
- Among those who received prenatal care, most (81%) started receiving care in their first trimester.
- And among those who received this care, the most common primary provider was an obstetrician (60%).
Prenatal class attendance differed over time and by subgroup
- More mothers attended prenatal classes in 2024 (33%) than in 2019 (24%).
- More mothers pregnant with their first child (45%) attended a prenatal class compared to mothers with at least one previous live birth (13%).
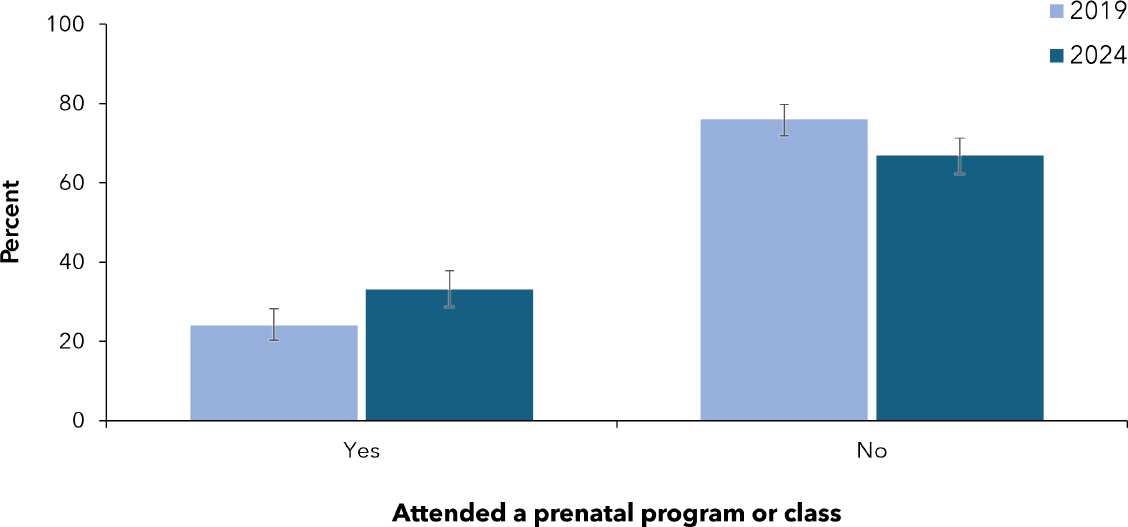
On third of mothers attended a prenatal program or class in 2024, which was higher than 2019
Notes: Vertical bars represent 95% confidence intervals.
Source: Peel Infant Feeding Survey, 2019, 2024, Peel Public Health.
Education and health care are important during the prenatal period
They support the best possible health outcomes and prepare for pregnancy, birth, and newborn care (refer to references 5 and 6).
Increasing prenatal education and supports matters
- Prenatal education and care can contribute to increased motivation, confidence, knowledge and skills around breastfeeding.
- Ensuring every mother has access to supportive prenatal care by addressing barriers and challenges is important for improving health outcomes.
Most infants were given a vitamin D supplement
In 2024, 84% of infants were given a vitamin D supplement every day or almost every day. This was similar to 2019 (78%). Refer to additional graphs.
Vitamin D supports healthy bone development
It’s recommended that infants less than one year of age receive at least 400 IU of Vitamin D per day which can be achieved through supplementation, formula, solid foods, or a combination of these sources.
For most breastfed infants, supplementation of 400 IU of Vitamin D per day is recommended (refer to references 4 and 7).
Vitamin D deficiency among infants in Peel is likely low
This is due to the high rate of vitamin D supplementation.
Reasons such as knowledge, cost, accessibility or other factors may impact Vitamin D supplementation. Understanding the role of these and other factors in Peel can inform how to support all infants in achieving the Vitamin D supplementation recommendations.
Most infants started solids within the recommended time frame
In 2024, 81% of infants were introduced solids within the recommended time of around 6 months (5 months to less than 7 months of age). This was similar to 2019 (76%). Refer to additional graphs.

![]()
Solid foods at around 6 months supports optimal health
Introducing solids too late can contribute to nutrient (for example, iron) deficiencies and introducing solids too early can impact the duration of breastfeeding (refer to reference 4).
Most infants were fed iron-rich foods
92% of infants who had started solid foods had been given iron-rich foods, similar to 2019 (90%).
Half of these infants were not receiving enough iron-rich foods
About 51% of infants who had been introduced to solid foods were given iron-rich foods twice a day or more while the other half were given iron-rich foods less than twice a day (49%). This was similar to 2019 (53% and 47%, respectively).

![]()
Iron is essential to growth and development
Iron supports growth and cognitive, neurological, motor, and behavioral development.
It’s recommended that infants who are eating solids are offered iron-rich foods at least two times per day (refer to references 4 and 8).
Understanding the impacts of knowledge, cost, accessibility or other factors on how often infants are offered iron-rich foods can inform strategies to support families in achieving this recommendation.
Other information
- Patnode CD, Henrikson NB, Webber EM, et al. Breastfeeding and Health Outcomes for Infants and Children: A Systematic Review. Pediatrics. 2025;156(1):e2025071516. doi:10.1542/peds.2025-071516
- Liu JZ, Liao MQ, Zheng L, Li HR, Su X, Feng YH, et al. Associations of breastfeeding with maternal and child health outcomes: umbrella review. The American Journal of Clinical Nutrition. 2025;122(4):1061–74. doi:10.1016/j.ajcnut.2025.07.027
- Statistics Canada. Table 18-10-0245-01 Monthly average retail prices for selected products [Internet]. Available from: doi.org/10.25318/1810024501-eng
- Health Canada. Nutrition for Healthy Term Infants: Recommendations from Birth to Six Months. Published September 13, 2012 [Updated 2025 Oct]. Accessed April 9, 2026. www.canada.ca/en/health-canada/services/canada-food-guide/resources/nutrition-healthy-term-infants/nutrition-healthy-term-infants-recommendations-birth-six-months.html
- Chapter 3: Care during Pregnancy in: Public Health Agency of Canada. Family-Centred Maternity and Newborn Care: National Guidelines [Internet]. Ottawa, ON: Public Health Agency of Canada; 2023 [cited 2026 Jun 29]. Available from: www.canada.ca/en/public-health/services/publications/healthy-living/maternity-newborn-care-guidelines-chapter-3.html#ac
- Kehinde J, O’Donnell C, Grealish A. The effectiveness of prenatal breastfeeding education on breastfeeding uptake postpartum: A systematic review. Midwifery. 2023 Mar;118:103579. doi:10.1016/j.midw.2022.103579
- Peel Public Health. Briefing note: Vitamin D supplementation recommendations from birth to six years of age. Mississauga (ON); 2020 Feb [Updated 2023 Nov].
- Health Canada. Nutrition for Healthy Term Infants: Recommendations from Six to 24 Months. Published September 13, 2012 [Updated 2025 Oct]. Accessed June 16, 2026. www.canada.ca/en/health-canada/services/canada-food-guide/resources/nutrition-healthy-term-infants/nutrition-healthy-term-infants-recommendations-birth-six-months/6-24-months.html#a23
The Peel Infant Feeding Survey (PIFS) collects data from mothers on infant feeding practices in hospital and at home, breastfeeding duration, any and exclusive breastfeeding, and introduction of other liquids and solids. The survey is run by Peel Public Health with data collection administered by CCI Research Inc. In 2019, 455 mothers were surveyed and in 2024, 419 mothers were surveyed.
In 2019, the survey was completed using a Computer-assisted Telephone Interview (CATI) system. In 2024, an online option was introduced and surveys were completed using either a CATI or a Computer-assisted Web Interviewing (CAWI) system. While efforts were made to ensure consistency between the telephone and online options, it is possible that response patterns differ between online and telephone respondents, for instance due to social desirability bias or question interpretation. This may impact the comparability of the 2024 cycle with the 2019 cycle.
Telephone surveys were administered in the respondent’s language of preference through the use of a professional language line. The online survey was available in English only.
Like any survey, data from PIFS can be impacted by non-response bias. Despite our sampling procedure, it is possible that those who chose to respond to the survey differed systematically from those who did not, resulting in a sample that may not be fully representative of the Peel population.
In the figures of this report, 95% confidence intervals are provided for many of the estimates (for instance, percentages). The confidence interval presents a lower and upper range of values that we are confident contains the value of the estimate for the population, 95% of the time, or 19 times out of 20.
Confidence intervals were used as a conservative method to determine statistical significance regarding differences between groups or years. When the 95% confidence interval of the estimate for one group or year does not overlap with that of the estimate for another group or year, the difference between the estimates is considered statistically significant (meaning it is unlikely to be due to chance). If the confidence intervals of two estimates do overlap, the estimates may still be significantly different; however, an appropriate statistical test would be required to assess whether there is a statistical difference between the two estimates. We did not conduct additional tests to determine significance in this report and therefore we acknowledge that some differences between groups may have been missed.
The statements ’higher or lower’ and ‘increased or decreased’ are found throughout the report to describe differences between groups or years. These statements highlight statistically significant differences in estimates.
In this report, data were not released due to a small number of respondents where there were less than 10 respondents with the outcome (numerator) or less than 20 to the overall question (denominator). Additionally, if the data underlying an estimate was spread out or very spread out, meaning there was moderate to high variability as determined by the coefficient of variation (CV), the estimate was either released with a warning to “use with caution” (CV between 15.0 and 35.0) or labeled as “not releasable” (CV greater than or equal to 35.1).
All estimates throughout this report exclude survey respondents who did not respond to one or more of the necessary questions for that calculation.
The use of terminology can have an important impact on health equity and the interpretation of health data. Our goal at Peel Public Health is to analyze and present health data in a meaningful way that does not produce or perpetuate harm. We strive to adapt as terminology and language evolves over time.
Definition of terms:
- In this report, breastfeeding is defined as any self-reported attempt to feed the infant at the breast, or feed breast milk or mother’s milk by cup, tube, or bottle. Breastfeeding initiation is measured by the question “Have you ever tried to feed your baby breast milk?”
- Exclusive breastfeeding is defined as breastfeeding only, without additional food or liquid (e.g., water, sugar water or formula) excluding vitamins, minerals, or required medication. By this definition, an infant would no longer be classified as exclusively breastfeeding after consuming only a single sip of any other liquid.
- Mothers (eligible for survey participation) were six to eight months postpartum at the initiation of this survey, residing in one of Peel’s municipalities, and 15 years of age or older. Those who had known involvement with the Children’s Aid Society or experienced a stillbirth or had a live born infant who died were not eligible to participate.